


|
ABSTRACTAims: The first aim of this study was to measure the extent of care planning and support for health goals within a sample of Māori/non-Māori people with long-term conditions (LTCs). The second aim was to compare those with and without care plans, and those with and without support for health goals, with respect to health and experiences with general practice. Background: Collaborative care planning, resulting in a written care plan, and providing support for patient-identified goals are important aspects of LTC management. In the MidCentral District Health Board region, primary care practitioners have had help to achieve this through the introduction of comprehensive assessment and care-planning tools. Methods: 569 people with at least one LTC, who had recently enrolled in a local EnhancedCare+ programme or were receiving care from an LTC community clinical nurse, were recruited into the region’s “Talking about Health” study, designed to explore LTC care from patient and provider perspectives. Consenting participants chose to complete a paper (by post) or electronic (email link) questionnaire, which included measures of health, healthy behaviours, experiences with doctors and nurses in general practice, patient activation, care planning/goal support and demographics. Results: People with written care plans were more active self-managers, reported better interactions with primary-care doctors and nurses, and perceived receiving more support from the general practice team than those without. Results were similar for people receiving support for their health goals, but differences in mental and physical health were also evident. More Māori than non-Māori reported having a written care plan, and support for health goals in the absence of a written care plan. A slightly broader range of benefits was evident for non-Māori than Māori, but the different sample sizes need to be taken into account when drawing conclusions. Conclusions: Written care plans and practitioner support for health goals appear to benefit people with LTCs. Support for health goals is important as, even without a written care plan, it was associated with better health and more positive ratings of practitioner interactions. Challenges for the region are to involve more people/whānau in collaborative care planning and to address system-wide barriers to embedding care-planning practices into routine care. |
||||||||
KEYWORDScare plans, practitioner support for health goals, long-term conditions, general practice, primary care, Māori |
|||||||||
 Melanie Taylor
 Claire Budge
 Chiquita Hansen
 Materoa Mar
 Folole Fai
INTRODUCTION
FOR MANY YEARS, HEALTH practitioners and services have been challenged to redesign the way they provide effective management of long-term conditions (LTCs), with self-management a priority. Like many countries, Aotearoa New Zealand has focused on self-management, with services directed to provide care that is person-centred. This means people take a lead role in their own care planning and feel supported to work in partnership with health professionals to set goals and make action plans (MOH, 2016). Self-management includes “the daily activities in which individuals engage, along with their family, community and health professionals, to manage a chronic illness” (Schulman-Green, Jaser, Park, & Whittemore, 2016, p1469). One of the most effective ways of helping people to self-manage their LTCs is to personalise and plan care with them, taking heed of each individual’s unique situation, abilities and aspirations. For Māori, this partnership should explore including the whānau (family), with whānau taking an active role in identifying their goals and steps towards hauora (well-being).
Literature review
Care planning is described by Burt et al (2012) as a collaborative process, where the patient and practitioner discuss diagnosis and treatment of the condition and formulate management goals together. Ideally, it should include support for self-management and behaviour change (Coulter et al, 2015). A care plan is a written document, recording the outcome of the care-planning process, that can serve as an extension of the medical record and as a guide to action that stimulates forward thinking and focuses on goals. It can also have a contractual purpose, such as advanced care planning during end-of-life care (Burt et al, 2014). While care-planning policy promotes capturing all of a patient’s needs using a holistic approach, in practice, care plans have often been implemented using a condition-specific approach, eg to better manage a person’s diabetes, rather than having a broader LTC focus (Burt et al, 2014; Lenzen, Daniels, van Bokhoven, van der Weijden, & Beurskens, 2017).
It is likely that care planning often takes place without a physical document being provided to the individual. The General Practice Patient Survey in the United Kingdom (UK) found 84 percent of patients with LTCs participated in care-planning discussions, while only 12 percent reported having a written care plan (Burt et al, 2012). Another UK study found that none of the 23 elderly patients with multiple LTCs reported explicit care-planning discussions or having a written care plan (Newbould et al, 2012). In several Australian states, care planning has been integrated into an automated, web-based collaborative, coordinated, care-management system. It was then found that patients were four times more likely than the national average to have their care plan followed up by regular review. In addition, general practitioners were more likely to follow evidence-based guidelines for those having regular reviews (90 percent compliance) than when working with patients with irregular or no care-planning reviews (50 percent compliance) (Precedence Healthcare, 2012). A recent study found that 63.7 percent of an Australian LTC sample indicated their health professional developed a plan of care with them “to a large or great extent” (Saunders, Carter, & Brown 2019). However, as noted earlier, developing a plan of care is qualitatively different to having a completed, written care plan.
Little information about the prevalence or outcomes of care planning for Māori or other ethnicities in Aotearoa New Zealand was found, but in a patient experience survey pilot conducted in a number of primary health organisations, only 30 percent of LTC respondents indicated they had a care plan and that it was followed up (HQSC, 2017). These figures relate to care-planning discussions and may or may not have resulted in an actual written plan.
The low uptake of care planning has been attributed to a variety of issues. The complexity of care-planning processes, the administrative burden it imposes and the potential lack of integration between care providers are all problematic (Harris & Zwar, 2007). Provider attitude can also contribute, with one study showing that practice nurses were sceptical about people’s ability to set their own goals and action plans (Kennedy et al, 2014). A conversation analysis of action-planning and goal-setting talk between practice nurses and patients found the care-planning process was often dominated by the health practitioner, with the patient normally playing a passive role and not invited to share their ideas (Lenzen et al, 2018). Thille, Ward and Russell (2014) found that commonly the practitioner framed the discussion by identifying the patients’ problems and proposing solutions in accordance with available services, rather than encouraging people to identify their own goals for improved health and well-being.
A Cochrane review of the benefits of care planning for people with LTCs (Coulter et al, 2015) found that the positive impact of care planning was greater when more stages of the process were completed, when contact with the health service was regular and when the person’s own health professional participated. Benefits of care planning have been identified as: lower use of health services, with a 22 percent reduction in risk of being hospitalised for diabetes (Caughey et al, 2016); improved patient access to allied health services (Wickramasinghe et al, 2013); and encouragement of practitioners to follow clinical guidelines (Caughey et al, 2016; Wickramasinghe et al, 2013).
Unfortunately, even when care is planned, it may be different to what patients want or need (Kuluski et al, 2013). This is particularly problematic for those who are elderly or have co-morbidities, as they are likely to have multidimensional needs that focus on overall well-being and functioning (Francis, Carryer, & Wilkinson, 2018; Vermunt, Harmsen, Westert, Rikkert, & Faber, 2017).
The need to embed both personal goal setting and care planning into a package of care was driven by the pioneers of early self-management work. Bodenheimer et al (2002) proposed that people changed their behaviours if they had confidence in their ability to do so, and Lorig and Holman (2003) found changes in self-efficacy to be associated with changes in health behaviour and health status. Goal setting is often used as a tool to promote behaviour change (Lenzen et al, 2018), requiring patients and practitioners to mutually agree on patients’ health-related goals with the aim of increasing motivation, confidence and understanding.
Confidence comes from prior and repeated success with small, realistic and person-specific goals. Patient-led problem-solving and goal setting, and efforts to enhance patient activation (ie the patient’s level of active engagement both in managing their own health and engaging with health services) have been associated with improvement in outcomes for some patients (Holman & Lorig, 2004; Hibbard, Stockard, Mahoney, & Tussler, 2004). Research has shown that patients who are informed about their options have a greater desire to be involved in decision-making than those who are uninformed (Stacey et al, 2011). To use a person-centred model, where the person’s agenda or goals are prioritised, takes a shift in practice, as traditional more directive models do not provide the motivation for change. Instead the approach should be a team-based, person-centred one, enabling people with LTCs to find their own solutions and the motivation to take responsibility for their own health (Funnell, 2000).
Research context
For the last decade, the Central Primary Health Organisation (PHO) (now known as THINK Hauora) and the MidCentral District Health Board (DHB) have been engaged in redesigning primary care services to make planned, systematic and proactive care, as advocated in the Chronic Care Model (Wagner, 1998), part of everyday LTC care. The redesign was aligned with the Ministry of Health’s “better, sooner, more convenient” policy (MOH, 2011) and included the introduction of a primary health care, LTC-focused, comprehensive health assessment tool (CHA) and patient care plan – with the assessment informing the content of the care plan. The assessment aimed to understand the individual’s experience of living with their LTCs, and to identify the determinants of health affecting their well-being. These assessment and planning tools became an integral part of the locally-funded EnhancedCare+ programme. To improve equity, practitioners were urged to prioritise entry for those who would benefit most from this LTC programme, including Māori and Pacific people. Practitioners were expected to partner with patients, to share decision-making and identify health goals and possible interventions in accordance with best practice and patient preference. Regular care-plan reviews and updates were also required.
Despite best intentions, design of the electronic tools was hampered by problems. Some practitioners thought the care plan was too complex to be useful, while others were frustrated with the protracted redesign process. Consequently, resistance to practice change became commonplace and this, combined with the increasing demands placed on general practice, resulted in varying degrees of implementation. The quality and frequency of assessment and care-plan review differed across practitioners and health services. However, care planning, based on good assessment and using the nursing process, continued to be encouraged to support best practice.
AIMS
The overall aim of this paper was to explore care planning and practitioner support for health goals within a sample of people with LTCs in general practice. Specifically, this meant:
- Identifying the extent to which written care plans are developed and reviewed, and to compare those participants with and without care plans with respect to self-reported health and ratings of their general practice interactions.
- Identifying the extent to which health goals are checked on or supported, and to compare those participants with and without support for health goals with respect to self-reported health and ratings of general practice interactions.
- Looking at the no care-plan group, to compare those with and without support for health goals with respect to self-reported health and ratings of general practice interactions.
Results are presented separately for Māori and non-Māori participants.
METHOD
The “Talking about Health” study gained approval from the Health & Disability Ethics Committee (HDEC) (ref. 16/NTA/32). Data were analysed using SPSS Statistics 20. No imputation of missing data was done. Means were calculated and chi-square and independent t-tests were performed to draw comparisons between groups.
Participants
Invitation letters were sent to all people aged 18 and over in the DHB region with a documented comprehensive health assessment during the previous three (Māori/Pacific) or two (other ethnicities) years (N=2730). The extended time period for Māori and Pacific people was implemented to encourage better representation. Interested individuals returned consent forms, and questionnaires were then sent out. An online option via SurveyMonkey was also provided.
Materials
The questionnaire for the Talking about Health study covered a wide range of topics related to health and self-management. The topics relating to the analyses in this study included general physical and mental health, healthy behaviours, patient activation, general practice experiences, care planning and support for health goals and demographics.
General health: The physical (GPH) and mental health (GMH) scales of the short form of the Patient-Reported Outcomes Measurement Information System (PROMIS; Hays, 2009) global health questionnaire were used. Each scale consists of four items, some rescaled and reverse-coded according to the scale instructions, with good internal consistency (GPH α=.81; GMH α=.86). Good validity was evidenced by correlations between PROMIS and the EQ-5D, a widely-used health-related quality-of-life measure (GPH r=.82; GMH r=.61). An additional question, seeking an overall rating, “How much does having one or more long-term conditions affect your quality of life?” was added, using a scale ranging from 0 (“no effect”) to 10 (“very large effect”).
Healthy behaviours: Use of a set of health-enhancing behaviours considered to be important to all people with LTCs was measured by asking respondents to indicate how many days each week, on average, they were carried out. A healthy behaviours scale was created by combining responses to questions about eating a balanced diet, eating fatty and sugary foods (reverse coded), doing gentle exercise, taking medication as advised and planning nice things to look forward to. Responses were averaged, allowing for one missing response, to produce a score ranging from 0-6.
Patient activation: Participants’ knowledge, skill, and confidence to manage their health were assessed using the Patient Activation Measure (PAM) (Hibbard et al, 2004). Respondents were asked to indicate how much they agreed with 13 statements, using a four-point scale ranging from “disagree strongly” to “agree strongly”, scored as 1 to 4, or “not applicable”. Scores were calculated using a spreadsheet provided by Insignia Health LLC, which generates scores ranging from 0 to 100. Most scores fall between 39 and 95 (Greene & Hibbard, 2012). The PAM has been shown to have good internal consistency, with alphas of .81 (Prey et al, 2016) and .78 (Magnezi, Glasser, Shalev, Sheiber, & Reuveni, 2014) reported. Good construct and criterion validity were initially reported (Hibbard et al, 2004) and scores have been associated with changes in patient outcomes (Greene, Hibbard, Sacks, Overton, & Parrotta, 2015).
General practice experiences (GPE): General practice experiences were assessed in relation to doctors and nurses separately, using nine questions from the New Zealand version of the General Practice Assessment Questionnaire (Zwier, 2013). Minor wording changes were made and five additional questions developed by the study team. The item stem was: “When you see the doctor/nurse at your practice, how good are they at . . .” and items covered various aspects of the consultation, including listening, spending enough time, being patient and knowing you as an individual. Response options ranged from “excellent” (6) to “very poor” (1). Two of the 14 questions (relating to involvement of family/whānau/fanau in decision-making and practitioners learning about social support needs) were considered to be not applicable by a number of respondents and the total general practitioner (GPE:GP) and nurse (GPE:N) scales were calculated allowing two missing responses to accommodate this, thus retaining as many cases as possible for analysis. An additional question asking for an overall rating of “How good is the care and support you get for managing your long-term conditions from the doctors and nurses at your general practice?” was added, measured on a 0 (“not at all good”) to 10 (“extremely good”) scale.
Care planning and support for health goals: Participants were asked to indicate if they had a written care plan (yes/no/unsure); and if so, whether they were involved in its development (yes/no); if it was used on a daily basis for self-management (yes/no); and whether it was reviewed with a health professional (yes/no); and if so, how often (tick box). Care planning was defined as “an agreement between you and your doctors and nurses to help you manage your health day-to-day. It is usually a written document you can carry with you to appointments and use at home. It can include information about your medicines, an eating or exercise plan, or goals you want to work towards, like returning to work or taking your medicines correctly. It will usually include steps towards managing your condition better”. They were also asked if a health professional checked on how they were getting on with their health goals and if they were supported in achieving them. Response options were “yes”/”no”/”I have no goals”.
Demographics: Ethnicity was measured as in the New Zealand Health Survey (MOH, 2014) and participants were allowed to select more than one option. Anyone identifying as Māori, or Māori and one or more other ethnicities was counted as Māori for this study. Age was measured starting at 18-24 then increasing in 10-year increments ending at 85+ years, and sex as male or female. Income adequacy was measured by asking whether their total household income was enough to meet everyday needs, with response options of “not enough”, “just enough”, “enough” and “more than enough”. Options for highest educational qualification were “no school qualifications”, “school qualifications”, “post school/polytech/trade qualification” and “university qualification”. A list of common long-term conditions was provided and participants were asked to indicate which they had. A space for additional conditions was provided.
Results
In this study, we explored both the activity and benefits of written care planning and practitioner support for health goals. Questionnaires were returned by 569 people (20.8 percent response rate). Participants were predominantly New Zealand or other European (82 percent), 15 percent were Māori and less than 1 percent Pacific. Just over half of the sample was female (56 percent) and the majority (62 percent) were aged between 65 and 84 years.
Written care plans
Of the 104 (18.7 percent) respondents who indicated they had a written care plan, 23.2 percent were Māori and 18.0 percent non-Māori. Another 365 (65.8 percent) did not have a written care plan and 86 (15.5 percent) were unsure. Of those with care plans, 89 percent said they had contributed to the care plan and 71.4 percent used it for day-to-day health management. The majority (83.5 percent) indicated that a health practitioner reviewed their care plan with them; frequency of review ranged from more often than quarterly (9.2 percent) to less than annually (9.2 percent). While the modal response was quarterly (37.9 percent), 27.9 percent said it was every 12 months or less. Most people with a care plan (81 percent) also said that a practitioner provided support in reaching their health goals.
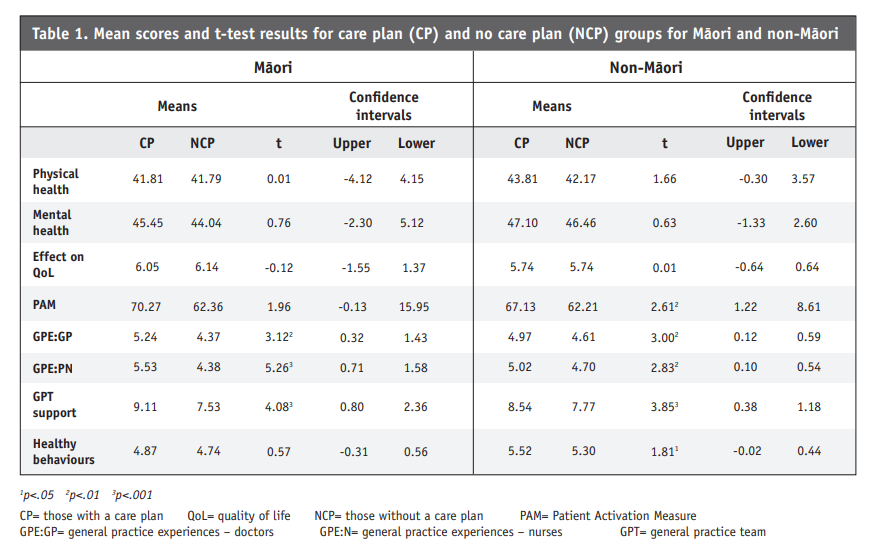
As it was likely that people with written care plans would be aware that they had them, those who indicated they were unsure were combined with those who indicated they did not have one. Demographic characteristics and scores on key study variables were then compared for these two groups: care plan (CP) and no care plan (NCP). Chi square analyses found no significant differences in the CP/NCP distribution according to sex, age, ethnicity, income adequacy or education. Also, no difference in mean number of LTCs was found between the two groups (CP M=3.4; NCP M=3.3) Independent t-tests were used to compare the care plan and no care plan groups within Māori (CP n=19; NCP n=63) and non-Māori (CP n=85; NCP n=388) separately (see Table 1). On average, Māori participants with a written care plan reported better interactions with doctors and nurses in primary care, as well as perceiving themselves to get more support from the general practice team than those without. The same was true for non-Māori, but in addition those with a care plan were more active self-managers and also indicated they engaged in healthy behaviours more frequently than those without. However in interpreting these findings, it is important to consider the smaller number of Māori participants and to look at the mean scores as well as the statistical test results. The difference in mean PAM scores is considerable for Māori, as well as for non-Māori.
Practitioner support for health goals
Practitioner support for health goals was also explored and, interestingly, 147 (28.5 percent of respondents) said they had no health goals – 24.7 percent of Māori and 29.2 percent of non-Māori. Half the sample said that a health professional regularly checked how they were getting on with their health goals and slightly more (51 percent) indicated they received support from a health professional to reach their goals. Responses to these two questions were combined to make a group who had a health professional checking on goals and/or providing support for them reaching their goals (identified as health goal support – HGS), and another group who indicated they had neither form of support (no health goal support – NHGS). No differences were found between the HGS (71.8 percent) and NHGS (28.2 percent) group membership with respect to ethnicity, age, educational level or income adequacy. However, men were more likely than women to say they received support from a health practitioner (χ2 (1, N= 369) = 5.00, p=.03).
Additional mean comparisons between the groups, for Māori (HGS n=45; NHGS n=37) and non-Māori (HGS n=244; NHGS n=243), are displayed in Table 2.
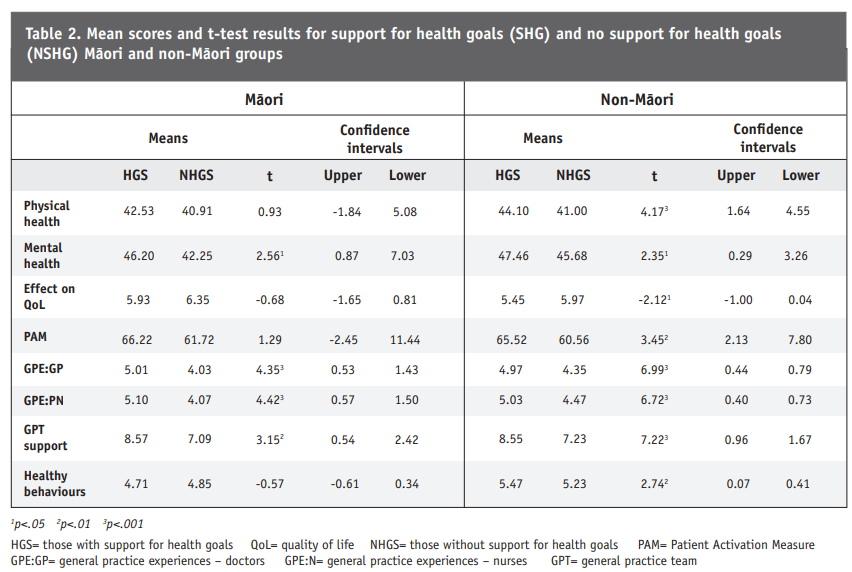
Māori who reported that a practitioner supported them in reaching their health goals were found to have better mental health, report more positive general practice experiences with both doctors and nurses and provided higher ratings of support received from the GPT than those without support for health goals. Looking at the means, there appeared to be a notable difference with respect to effect on quality of life and PAM scores for Māori as well. The non-Māori results indicated that the health goal support group was better off with respect to all the comparisons than the group without support.
A closer look at the no care plan group
The group who indicated they either had no written care plan or were unsure about it, were divided into two groups as before – those with a practitioner checking on or supporting them in reaching their health goals (HGS) and those without (NHGS). The latter group included those people who said they had no health goals. The two groups were compared on the same measures and the results, for Māori (HGS n=26; NHGS n=37) and non-Māori (HGS n=177; NHGS n=211) separately as before, appear in Table 3.
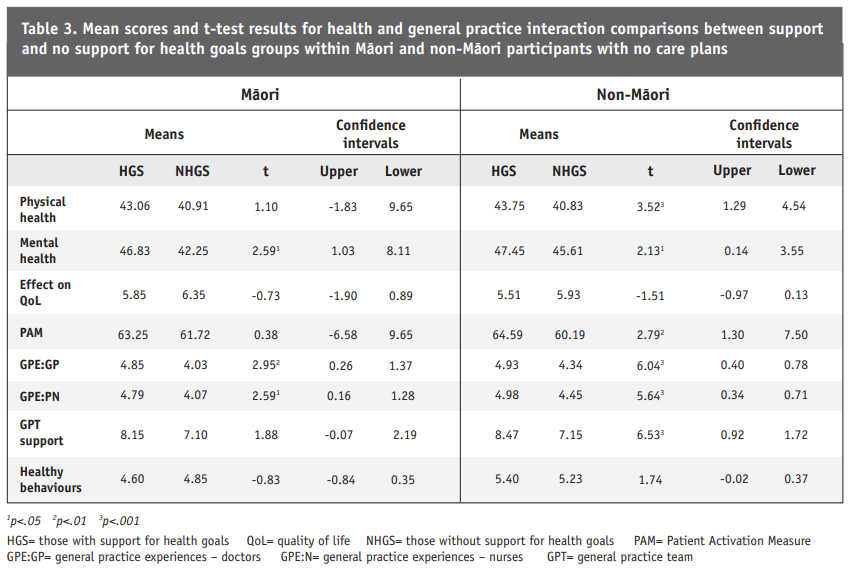
These results suggest that even in the absence of formalised care planning, support for health goals is important. Māori participants who indicated they did receive health goal support reported better mental health and more positive general practice experiences than those without. For non-Māori, health goal support was associated with better physical and mental health, a higher level of activation and more positive general practice experiences and support from the general practice team.
DISCUSSION
The focus in this study was on exploring the extent to which written care plans are developed with people with LTCs and then given to them to assist with self-management. The emphasis was on written care plans, as care-planning discussions, even if documented in patient notes, may benefit practitioners in following up on treatment but are unlikely to help patients manage their conditions at home – something they need to do on a daily basis.
In this study, the number of participants with a written care plan was disappointing, only 18.7 percent reporting they had one, with a further 15.5 percent being unsure. This proportion is, however, comparable to that found by Burt et al (2012) in the United Kingdom. While slightly more Māori reported having a care plan (23.2 percent), there is room for considerable improvement in light of the DHB region’s goal of improving equity and providing better LTC care, and improving this number would be a good goal to work towards. The development of a care plan was a compulsory requirement of the EnhancedCare+ programme and at the time, good leadership promoted the principles of effective patient engagement, self-management and self-management support. It is likely that the inability to provide electronic tools that practitioners liked and would use affected the uptake; however, other reasons may have contributed, such as a lack of time within the consultation. It is also possible that not all practitioners consider care planning to be part of their role, and some may assume it is being carried out by another member of the multidisciplinary team. Other likely contributing factors could be the many demands placed on general practice and a reluctance to change from familiar service-delivery models – primarily those focused on acute care delivery. The finding that there was no difference in the number of LTCs experienced by those with and without a care plan is interesting and warrants further investigation. It may be that certain practitioners routinely engage in care planning, while others do not, and that the patient’s complexity level does not alter standard practices. Blakeman et al (2006) note that practitioners may not be prepared to invest energy into care planning if they don’t consider the evidence warrants it.
A large proportion of people with care plans reported contributing to the care plan, which is a key feature of the goal-setting and review process (Cramm & Nieboer, 2015; Funnell, 2000; Sidani & Fox, 2014). Regular review with the individual/whānau accommodates changing needs and enables important support to be provided (Morgan et al, 2016). However, a small group of participants (11 percent) reported having no involvement in care planning, which may indicate a lack of collaboration between the individual and practitioner in deciding on health goals and how to achieve them. Likewise, a small group said that they didn’t participate in a care-plan review (16.5 percent). While 71 percent of people with care plans reported using it to help manage their health day to day, close to a third did not. We have to ask why not. Perhaps the care plans were not understood, written simply enough, realistic or individualised enough to be meaningful. Alternatively, the link to management at home may not have been made, particularly if the person did not feel appropriately involved and listened to in care-planning conversations.
The importance of collaborative goal setting and practitioner support for achieving goals was promoted within care-planning education. It was assumed that at least this could be integrated into practice, even if more extensive care planning was not. Unfortunately, it appears that only half of the group was supported in this way, and we were surprised by the finding that almost a third said they had no health goals at all. While the rate was slightly lower for Māori, perhaps indicating that more conversations were held, health literacy might be a contributing factor (as “health goals” were not explicitly defined in the questionnaire), or people may have forgotten that a conversation took place. Likewise, people may have resisted practitioner suggestions for behaviour change and consequently no goals were set. Weariness could also be a factor, particularly with co-morbidity, as “patients have to force themselves to accomplish previously effortless physical tasks that become harder and harder as time passes” (Francis et al, 2018, p4). More likely, practitioners chose not to meet the programme requirements, found that conversations on care planning or goal setting were difficult, or were not invested in providing self-management support (Cramm & Nieboer, 2015).
A second focus was on the benefits of having written care plans and/or support for health goals and these were apparent when comparisons of mean scores were made. Those with care plans rated their general practice experiences and support more highly, and non-Māori had higher activation and engaged in healthier behaviours, then those without. Having support for health goals showed a similar pattern of means, with better mental health for both ethnicities also being included.
A potentially important finding was that for the group without a written care plan, having practitioner support for health goals was still of benefit. Better mental health was identified for Māori and non-Māori, as well as higher ratings of general practice experiences. Additional differences were found for the larger non-Māori group. Further exploration of this would be beneficial, especially as there appears to be a dearth of literature on the benefits of practitioners providing support for patient-centred health goals.
The small number of Māori included in the study must be acknowledged, as the magnitude of the means show similar effects for both Māori and non-Māori in general. It is also important to acknowledge the more complex experience and definition of health for Māori with “self-management” encompassing support from whānau in its broadest meaning. Involving whānau in consultations, planning and support for goal setting, and ensuring they are prioritised for LTC care, is essential to support Māori – both with behaviour change activities and with their overall ability to manage LTCs on a daily basis. Cram, Smith and Johnstone (2003) identified the importance for Māori of receiving understandable – including visual – information, and receiving support and follow-up when accessing health services and making behavioural changes. These are clearly integral to the care-planning process. Pitama, Huria and Lacey (2014) describe an indigenous health framework which, based on a revised Meihana Model and the hui process, supports practitioners working with Māori people and their whānau to improve health outcomes.
The identified poor uptake of care planning may be indicative of a bigger issue. Practitioners want people to take responsibility for their own health; however, it appears that they themselves may be unwilling to undergo the level of practice change necessary for this to occur. Self-management does not magically happen, but requires concerted effort by practitioners and practice teams to help people develop the knowledge and skills required, and gain the confidence to act on them.
Limitations
The low response rate is a major limitation of this study, as the sample cannot be considered representative of the study population. This is particularly true for the Māori subsample, and consequently it is more important to look at the magnitude of the mean differences as they may provide a better sense of the effect size than the significance of the t-test results. For example, with respect to the patient activation findings, a 5-point difference in scores is considered to be of clinical significance (Fowles, Terry, Xi, Hibbard, Bloom, & Harvey, 2009) and this was found in the current study for both ethnicities. The sample is only taken from the MidCentral DHB region, which limits its broader generalisability. While “care plans” were described simply, we did not define “health goals” and this may have had some impact on participants’ responses. The study was self-report, and data is therefore prone to the same biases as any other self-report research. However, it is difficult to collect this type of information in other ways, given that our interest was in people’s perceptions of their own health and self-management and the general practice-based care they receive for their LTCs.
CONCLUSIONS
The identified benefits for patients who have a written care plan, or who receive support in achieving health goals, endorse the widespread need for these tools to be used in practice. Improved health and well-being, quality of life, experiences with general practice, and self-management ability are potentially life changing, and support the New Zealand Health Strategy’s vision “to enable people to live well, stay well and get well” (MOH, 2016). Coulter, Locock, Zieband and Calabrese (2014) urge that patient experience data such as this be used to enhance care provision rather than just being collected for research; hence it is very important that these findings benefit clinical practice. Tips for effective care planning and goal setting in clinical practice have been appended. These are based on literature, the first author’s years of experience working in this field and from talking to patients and practitioners in primary care.
Based on our study, improvements suggested to the PHO included those that would increase the number of people having access to these tools and level of support and to prioritise Māori in order to improve health inequalities. Unfortunately, its realisation relies on the interplay of many complex factors including: having tools that practitioners like and have been educated to use; practitioners having dedicated time to be able to do this work and provide follow-up; and changing the consultation talk so that people can set their own goals, rather than those of the practitioner. In our view, it is only then that we will see more success in embedding written care plans and goal setting into every-day practice.
Acknowledgment: The authors would like to acknowledge the anonymous reviewers for their helpful comments.
REFERENCES
Bodenheimer, T., Lorig, K., Holman, H., & Grumbach, K. (2002). Patient self-management of chronic disease in primary care. JAMA, 288(19), 2469-2475.
Blakeman, T., Macdonald, W., Bower, P., Gately, C., & Chew-Graham C. (2006). A qualitative study of GPs’ attitudes to self-management of chronic disease. British Journal of General Practice, 56(527), 407–14.
Burt, J., Rick, J., Blakeman, T., Protheroe, J., Roland, M., & Bower, P. (2014). Care plans and care planning in long term conditions: a conceptual model. Primary Health Care Research & Development, 15(4), 342-354.
Burt, J., Roland, M., Paddison, C., Reeves, D., Campbell, J., Abel, G., & Bower, P. (2012). Prevalence and benefits of care plans and care planning for people with long-term conditions in England. Journal of Health Services Research & Policy, 17(Suppl 1), 64-71.
Caughey, G. E., Vitry, A. L., Ramsay, E. N., Gilbert, A. L., Shakib, S., Ryan, P., Esterman, A., McDermott, R. A., & Roughead, E. E. (2016). Effect of a general practitioner management plan on health outcomes and hospitalisations in older patients with diabetes. Internal Medicine Journal, 46(12), 1430-1436.
Coulter, A., Entwistle, V. A., Eccles, A., Ryan, S., Shepperd, S., & Perera, R. (2015). Personalised care planning for adults with chronic or long-term health conditions. Cochrane Database of Systematic Reviews, 3(3), CD010523.
Coulter, A,. Locock, L., Ziebland, S., & Calabrese, J. (2014). Collecting data on patient experience is not enough: they must be used to improve care. British Medical Journal, 348, g2225.
Cram, F., Smith, L., & Johnstone, W. (2003). Mapping the themes of Māori talk about health. New Zealand Medical Journal, 116(1170).
Cramm, J. M., & Nieboer, A. P. (2015). Chronically ill patients’ self-management abilities to maintain overall well-being: what is needed to take the next step in the primary care setting? BMC Family Practice, 16, 123.
Fowles, J. B., Terry, P., Xi, M., Hibbard, J., Bloom, C. T., & Harvey, L. (2009). Measuring self-management of patients’ and employees’ health: further validation of the Patient Activation Measure (PAM) based on its relation to employee characteristics. Patient Education and Counseling, 77, 116-129.
Francis, H., Carryer, J., & Wilkinson, J. (2018). Patient expertise: Contested territory in the realm of long-term condition care. Chronic Illness, 15(3), 197-209.
Funnell, M. M. (2000). Helping patients take charge of their chronic illnesses. Family Practice Management, 7(3), 47-51.
Greene, J., & Hibbard, J. H. (2012). Why does patient activation matter? An examination of the relationships between patient activation and health-related outcomes. Journal of General Internal Medicine, 27(5), 520–526.
Greene, J., Hibbard, J., Sacks, R., Overton, V., & Parrotta, C. D. (2015). When patient activation levels change, health outcomes and costs change, too. Health Affairs, 34(3), 431-437.
Harris, M. F., & Zwar, N. A. (2007). Care of patients with chronic disease: the challenge for general practice. Medical Journal of Australia, 187(2,) 104-107.
Hays, R. D., Bjorner, J. B., Revicki, D. A., Spritzer, K. L., & Cella, D. (2009). Development of physical and mental health summary scores from the patient-reported outcomes measurement information system (PROMIS) global items. Quality of Life Research, 18(7), 873-880.
Health Quality & Safety Commission (HQSC). (2017). Primary care patient experience survey: Results from the first year of pilots.
Hibbard, J. H., Stockard, J., Mahoney, E. R., & Tusler, M. (2004). Development of the Patient Activation Measure (PAM): Conceptualizing and measuring activation in patients and consumers. Health Services Research, 39(4pt1), 1005-1026.
Holman. H., & Lorig, K. (2004). Patient self-management: a key to effectiveness and efficiency in care of chronic disease. Public Health Reports, 119(3), 239-243.
Kennedy, A., Rogers, A., Bowen, R., Lee, V., Blakeman, T., Gardner, C., . . . Chew-Graham, C. (2014). Implementing, embedding and integrating self-management support tools for people with long-term conditions in primary care nursing: a qualitative study. International Journal of Nursing Studies, 51(8), 1103-1113.
Kuluski, K., Gill, A., Naganathan, G., Upshur, R., Jaakkimainen, R. L., & Wodchis, W. P. (2013). A qualitative descriptive study on the alignment of care goals between older persons with multi-morbidities, their family physicians and informal caregivers. BMC Family Practice, 14, 133.
Lenzen, S. A., Daniëls, R., van Bokhoven, M. A., van der Weijden, T., & Beurskens, A. (2017). Disentangling self-management goal setting and action planning: A scoping review. PLoS ONE, 12(11), e0188822.
Lenzen, S. A., Stommel, W., Daniëls, R., van Bokhoven, M. A., van der Weijden, T., & Beurskens, A. (2018). Ascribing patients a passive role: Conversation analysis of practice nurses’ and patients’ goal setting and action planning talk. Research in Nursing & Health, 41(4), 389-397.
Lorig, K. R., & Holman, H. (2003). Self-management education: History, definition, outcomes, and mechanisms. Annals of Behavioral Medicine, 26(1), 1-7.
Magnezi, R., Glasser, S., Shalev, H., Sheiber, A., & Reuveni, H. (2014). Patient activation, depression and quality of life. Patient Education and Counseling, 94, 432-437.
Ministry of Health (MOH). (2011). Better, Sooner, More Convenient Health Care in the Community.
Ministry of Health (MOH). (2014). New Zealand Health Survey.
Ministry of Health (MOH). (2016). Self-management Support for People with Long-term Conditions (2nd ed).
Morgan, H. M., Entwistle, V. A., Cribb, A., Christmas, S., Owens, J., Skea, Z. C., & Watt, I. S. (2016). We need to talk about purpose: a critical interpretive synthesis of health and social care professionals’ approaches to self-management support for people with long-term conditions. Health Expectations, 20(2), 243-259.
Newbould, J., Burt, J., Bower, P., Blakeman, T., Kennedy, A., Rogers, A., & Roland, M. (2012). Experiences of care planning in England: interviews with patients with long term conditions. BMC Family Practice, 13, 71.
Pitama, S., Huria, T., & Lacey, C. (2014). Improving Māori health through clinical assessment: Waikare o te Waka o Meihana. New Zealand Medical Journal, 127(1393), 117-129.
Precedence Healthcare. (2012). Digital Regions Initiative cdmNet Australia. Final Report July 2009 – September 2012. Australian Government, Department of Broadband, Communications and the Digital Economy.
Prey, J. E., Qian, M., Restaino, S., Hibbard, J., Bakken, S., Schnall, R., . . . Creber, R. (2016). Reliability and validity of the patient activation measure in hospitalized patients. Patient Education and Counseling, 99(12), 2026-2033.
Saunders, C., Carter, D., & Brown, J. J. (2019). Primary care experience of older Australians with chronic illness. Australian Journal of Primary Health, 25(1), 13-18.
Schulman-Green, D., Jaser, S. S., Park, C., & Whittemore, R. (2016). A metasynthesis of factors affecting self-management of chronic illness. Journal of Advanced Nursing, 72(7), 1469-1489.
Sidani, S., & Fox, M. (2014). Patient-centred care: clarification of its specific elements to facilitate interprofessional care. Journal of Interprofessional Care, 28(2), 134-41.
Stacey, D., Bennett, C. L., Barry, M. J., Col, N. F., Eden, K. B., Holmes-Rovner, M., . . . Thomson, R. (2011). Decision aids for people facing health treatment or screening decisions. Cochrane Database Systematic Reviews, 10, CD001431.
Thille, P., Ward, N., & Russell, G. (2014). Self-management support in primary care: Enactments, disruptions, and conversational consequences. Social Science & Medicine, 108, 97-105.
Vermunt, N. P. C. A., Harmsen, M., Westert, G. P., Rikkert, M. G. M. O., & Faber, M. J. (2017). Collaborative goal setting with elderly patients with chronic disease or multimorbidity: a systematic review. BMC Geriatrics, 17, 167.
Wagner, E. H. (1998). Chronic disease management: What will it take to improve care for chronic illness? Effective Clinical Practice, 1(1), 2-4.
Wickramasinghe, L. K., Schattner, P., Hibbert, M. E., Enticott, J. C., Georgeff, M. P., & Russell, G. M. (2013). Impact on diabetes management of General Practice Management Plans, Team Care Arrangements and reviews. Medical Journal of Australia, 199(4), 261-265.
Zwier, G. (2013). A standardized and validated patient survey in primary care: Introducing the New Zealand General Practice Assessment Questionnaire (NZGPAQ). New Zealand Medical Journal, 126(1372), 47-54.
APPENDIX
| Common problems | Recommended practice |
|---|---|
| The practitioner identifies problems or conditions and wants to use these as a basis for goal-setting. |
|
| The practitioner takes the lead throughout the discussion. |
|
| The person feels unsupported. |
|
| Health goals are not documented. |
|
| The person’s health literacy requirements are not met. |
|
| An individual condition approach, rather than a broader, holistic, multimorbidity LTC approach is taken. |
|
| The care plan is not meeting the person’s needs. |
|
| The care plan is not reviewed regularly. |
|
| The practitioner is unsure of the process or lacks confidence to have care-planning or goal-setting conversations. |
|
| Practitioner/practice team is unable to provide self-management support within the current care-delivery model. |
|
Daily doses – uncut news
| 14 Sept |
WellSouth's Newborn Enrolment Kahu Taurima Programme a finalist at the Primary Care Awards 2026WellSouth's Newborn Enrolment Kahu Taurima Programme is a finalist at the Primary Care Awards for the HALEO Best Supplier Service, Product or Campaign category. Winners will be announced on 17 October. |
| 14 Sept |
Global Study: Nursing Shortages Require Workforce Policy Solutions, Not Recruitment Campaigns AloneWhy people choose nursing, and why they leave, comes down to the same factors. The global nursing shortage cannot be solved simply by encouraging more people to enter the profession, according to a new evidence brief. |
| 8 Sept |
Overworked, understaffed Gisborne ED staff strike Health and safety concerns arising from unsafe staffing levels have forced nurses at Gisborne Hospital’s emergency department (ED) to go on strike. |
| 4 Sept |
Strong growth in wāhine Māori and Pacific women’s cervical screening rates highlights success of self-testing programmeCervical screening participation has increased significantly for both wāhine Māori and Pacific women, reflecting the strong impact of self-testing, Screening Services and the dedicated efforts of health providers working alongside their communities. |
| 4 Sept |
Government must adopt Wai 2713 recommendations on disability systemThe Coalition Government must urgently adopt new recommendations from the Waitangi Tribunal which has found significant parts of the disability system prejudice tāngata whaikaha Māori (Māori with disabilities), NZNO says. |
| 31 Aug |
Employing graduate nurses will help keep them in nursing and the countryA new proposal that will require Te Whatu Ora to offer all eligible graduate nurses jobs in the public health system will help keep them in nursing and in Aotearoa New Zealand, NZNO says. |
| 26 Aug |
Health Minister’s claim Winter Plan ‘managing well’ delusionalHealth Minister Simeon Brown’s claim that hospitals are ‘managing well’ because of the Government’s Winter Plan is delusional, NZNO says. |
| 25 Aug |
Hospital data shows nursing shortages continue to put patients at riskTe Whatu Ora data released today shows patients are continuing to be put at risk by the Coalition Government’s deliberate failure to safely staff hospital wards, NZNO says. |
| 24 Aug |
Fed-up North Shore ED staff declare state of emergencyNZNO members working in the emergency department (ED) at North Shore Hospital have declared a state of emergency due to unsafe staffing levels resulting in ongoing overcrowding. |
| 19 Aug |
What happened to the winter health plan?The $25 million 2026 Winter Plan launched by Health Minister Simeon Brown in March to erase pressure on the health system has been an unmitigated disaster, Tōpūtanga Tapuhi Kaitiaki o Aotearoa NZNO says. |
| 11 Aug |
Applications open for advanced nursing education programmesHealth New Zealand is encouraging registered nurses to apply for two advanced education programmes that support nurses to further develop their clinical skills and expand access to care in communities across New Zealand. |
| 3 Aug |
Health New Zealand welcomes settlement of NZRDA collective agreementHealth New Zealand welcomes the vote by New Zealand Resident Doctors Association (NZRDA) members to settle their collective agreement. |
| 30 Jul |
Backing our frontline rural health workforceRural communities across New Zealand will benefit from three new investments that will support the rural health workforce and help more people access care closer to home, Associate Health Minister Matt Doocey says. |
| 22 Jul |
Te Whatu Ora must disclose staffing levels at time of tragic deathTe Whatu Ora must disclose whether the Waikato emergency department (ED) was short-staffed at the time a man tragically died in the waiting room, NZNO says. |
| 6 Jul |
Reflecting on IND 2026Looking back on last month’s International Nurses Day 12 May 2026 (IND 2026), the impact of this year's theme "Our Nurses. Our Future. Empowered Nurses Save Lives" continues to resonate across the world. ICN’s landmark IND 2026 report defined seven key powers of nursing and this message has been strengthened with nurses in every region celebrating, naming, and owning their powers throughout May. |
| 3 Jul |
Health New Zealand acknowledges Ombudsman statement on Wakari Ward 10AHealth NZ welcomes the independent investigation by the Ministry of Health into Ward 10A. On Wednesday the Health NZ board agreed to close Wakari Ward 10a as a forensic intellectual disability (ID) unit, with the future use of the ward yet to be determined. |
| 2 Jul |
New programme to fast track bowel cancer care and cut colonoscopy waitlistsHealth New Zealand is today launching a national initiative, designed to fast track bowel cancer care and reduce colonoscopy waitlists by up to 30 per cent. |
| 1 Jul |
Six new Co-Response Team locations announced to strengthen support for people in mental distressThe next six locations for Health New Zealand and NZ Police Co-Response Teams have been confirmed, expanding a model that helps people experiencing mental distress receive timely, wraparound support that better meets their health needs. |
| 29 Jun |
Mental health and addiction targets progress continuesHealth New Zealand continues to make important progress against its mental health and addiction targets, meeting four out of five national targets this quarter. |
| 25 Jun |
Access to care continuing to improve across a range of health indicatorsNew health data released today shows continued improvement in access to care across a range of health indicators. |
| 18 Jun |
Funding "boost" continues dangerous under-funding of aged careThe Health Minister’s funding "boost" for aged residential care continues underfunding to the sector and will continue unsafe practices and short staffing, which is putting vulnerable residents at risk, NZNO says. |
| 16 Jun |
Labour to make maternity scans freeLabour will add free maternity scans to the Medicard alongside three free doctor’s visits a year, so every pregnant woman gets the care she needs. |
| 29 May |
WellSouth Statement on Budget 2026: a missed opportunityBudget 2026 is a missed opportunity for primary care, and for the communities that depend on it most, in particular our rural people and practices. |
| 29 May |
Updated - Nurses on front lines of Ebola outbreak at serious riskIn response to the gravely concerning and escalating Ebola outbreak in the Democratic Republic of the Congo (DRC) and Uganda, the International Council of Nurses (ICN) warns that nurses and other frontline health workers are being put at serious risk and left fearful for their safety. |
| 27 May |
Health NZ committed to safeguarding patient informationHealth New Zealand welcomes the reports released today into the Manage My Health (MMH) cyber incident and is committed to ensuring all possible steps are taken to safeguard patient information. |
| 22 May |
More New Zealanders could benefit from funded vaccines from 2027Pharmac is proposing changes that would give more New Zealanders access to funded vaccines from 2027, including expanded access to the flu vaccine for young children. |
| 21 May |
It’s not just the wallet: How the gender pay gap can hurt women’s bodiesWhile many aspects of New Zealand’s enduring gender pay gap have been discussed, its physical impact on workers has been largely overlooked – until now. |
| 21 May |
Bupa nurses take pay equity claim over historic wage discriminationNZNO nurses working at Bupa aged residential care homes throughout Aotearoa New Zealand have raised a pay equity claim to address historic gender-based wage discrimination. |
| 20 May |
Waikato Hospital adds 10 forensic mental health beds Ten new forensic inpatient beds have been made available at the Regional Forensic Psychiatric Service at Waikato Hospital to expand forensic mental health capacity for adults in prison or on remand in Health New Zealand’s Midland region. |
| 18 May |
Strong gains in two-year immunisation target for Tamariki MāoriHealth New Zealand is welcoming a significant increase in Māori immunisation rates, with full immunisation at 24 months rising from just over 60 per cent in late 2024 to 71.5 per cent at the end of last month. |
| 15 May |
New global report shows empowering nurses is key to saving lives and strengthening health systemsAs the world marks International Nurses Day, the International Council of Nurses (ICN) is calling for urgent investment in nursing, supported by a major new global report, Our Nurses. Our Future. Empowered Nurses Save Lives, that presents seven key nursing powers. |
| 14 May |
Lakes and Whanganui nurses still waiting for Holiday Pay a decade on
Photo by Fin Ocheduszko-Brown at Whanganui Chronicle Nurses at Lakes and Whanganui districts are calling on Te Whatu Ora to explain why after a decade of redress, they still don’t know when they will receive their full Holiday Act remediation payments, NZNO says. |
| 13 May |
Recognising the extraordinary contribution of nursesInternational Nurses Day is an opportunity to recognise the extraordinary role nurses play in caring for New Zealanders at every stage of life, Health Minister Simeon Brown says. |
| 12 May |
Government’s decision to scrap fees free scheme will lead to further student exodusThe Coalition Government’s decision to scrap the fees free policy for third year tertiary students has left nursing tauira outraged |
| 30 Apr |
BroPilot grounding digital tools in whānau, culture, and care A passion for his Māori culture and a desire to make AI accessible to everyone inspired Troy Baker, Senior ICT Specialist, Health New Zealand to develop BroPilot – a culturally grounded way of working with Microsoft Copilot that reflects Māori values, whakaaro, and real lived experience. |
| 29 Apr |
Heartbreaking tragedies were avoidable - NZNOAnalysis by a media outlet, published today, finding health care staff shortages were contributing factors in the deaths of 11 babies is a national and avoidable tragedy, NZNO says. |
| 28 Apr |
CTU launches Roving Health and Safety Representatives policy on Workers’ Memorial DayThe New Zealand Council of Trade Unions Te Kauae Kaimahi has today launched our Roving Health and Safety Representatives policy at the Workers’ Memorial Day commemoration in Wellington, with further events held across the motu in Manawatū, Christchurch, and Otago. |
| 24 Apr |
“The 80s Calling”: New national campaign challenges outdated HIV stigmaAssociate Health Minister Matt Doocey today launched Health New Zealand’s “The 80s Calling”; a provocative new campaign designed to reduce stigma, normalise conversations about HIV, and support people living with HIV. |
| 23 Apr |
Government’s attack on Māori health raised at the UNConcerns over the Coalition Government’s active reversal of policies designed to improve Māori health outcomes were raised at the United Nations in New York this morning. |
| 16 Apr |
Tribute to Professor Lester Levy’s service to healthcareHealth New Zealand Chief Executive Dr Dale Bramley is paying tribute to Health NZ Board Chair Professor Lester Levy, who finishes in the role at the end of the month. |
| 10 Apr |
Chronic health care assistant short staffing harming vulnerable patientsTe Whatu Ora’s attempt to cut costs by requiring health care assistants to carry out cohort patient watches is harming vulnerable patients and staff, NZNO says. |
| 9 Apr |
New group education clinics speeding up knee and hip surgery careHealth New Zealand is rolling out a new group education approach for people waiting for hip and knee surgery in north and west Auckland, resulting in more patients being seen sooner. |
| 25 Mar |
National Diabetes Roadmap launched to improve care, prevention, and quality of lifeHealth New Zealand has launched a new National Diabetes Roadmap (‘the Roadmap’) to improve care, strengthen prevention, and support better health outcomes and quality of life for people living with diabetes. |
| 24 Mar |
ACT should leave nursing to professionals and medical evidenceTōpūtanga Tapuhi Kaitiaki o Aotearoa NZNO Kaiwhakahaere Kerri Nuku says ACT MP Todd Stephenson has dismissed the Nursing Council’s draft code of conduct - which proposes strengthening cultural safety, whānau-centred care and te Tiriti o Waitangi obligations - as political ideology. |
| 23 Mar |
UK report reflects ICN warnings on international recruitment ripoff — now countries must act togetherThe International Council of Nurses (ICN) warmly welcomes a new report from the UK All Party Parliamentary Group (APPG) on Global Health and Security that recognizes the huge sums saved by high-income countries who recruit abroad and acknowledges the severe harms caused by unethical recruitment from fragile source countries left without nurses. |
| 20 Mar |
HPV self-test boosts cervical cancer screening ‘across the board’, new study confirmsMaking human papillomavirus (HPV) self-testing available to all women increases the number of people screened for cervical cancer, a new study led by researchers from Te Herenga Waka—Victoria University of Wellington has confirmed. |
| 19 Mar |
ICN at CSW70: Violence against nurses is a gendered crisis threatening global healthThe International Council of Nurses (ICN) has warned that violence against nurses is a global gendered crisis that threatens health systems, patient safety and workforce sustainability |
| 17 Mar |
Additional winter health care workers a drop in the ocean of needThe Government’s announcement today of 378 extra staff to help hospitals cope with winter demand is a drop in the ocean of what patients need, NZNO says. |
| 12 Mar |
Funding change will ensure more consistent emergency care for New ZealandersA simple change in how ambulance medicines are funded is set to create more consistent emergency care. |
| 9 Mar |
Questions over dilapidated and cramped renal unit forced to ration dialysisThe Health Minister must explain why after years of concerns from nurses about Christchurch Hospital’s barely functioning dialysis unit, he only stepped in late yesterday when life-saving treatment had to be rationed, NZNO says. |
| 3 Mar |
Hospitals and health workers should never be targetsThe right of health care workers to provide care during international conflicts must be protected, Tōpūtanga Tapuhi Kaitiaki o Aotearoa NZNO says. |
| 2 Mar |
Public and Mental Health Nurses settle collective agreementHealth New Zealand welcomes the ratification of the two Public Service Association (PSA) Public and Mental Health Nurses collective employment agreements for Auckland and the Rest of New Zealand. |

